















A frenum (also called a frenulum) is a small band of tissue that connects your lip or tongue to nearby parts of the mouth. A frenotomy is a simple release of a tight frenum, while a frenectomy removes or reshapes it. Treatment is only worth considering when the band causes real problems with feeding, speech, comfort, or dental health—not just because it looks short or tight.
The main thing to know: Most frenums are normal and harmless. Surgery is an option only when a tight or thick frenum limits movement or causes symptoms.
What a Frenum Is and Where It Appears
Everyone has these small bands of tissue. They are part of normal mouth structure.
The most common ones are:
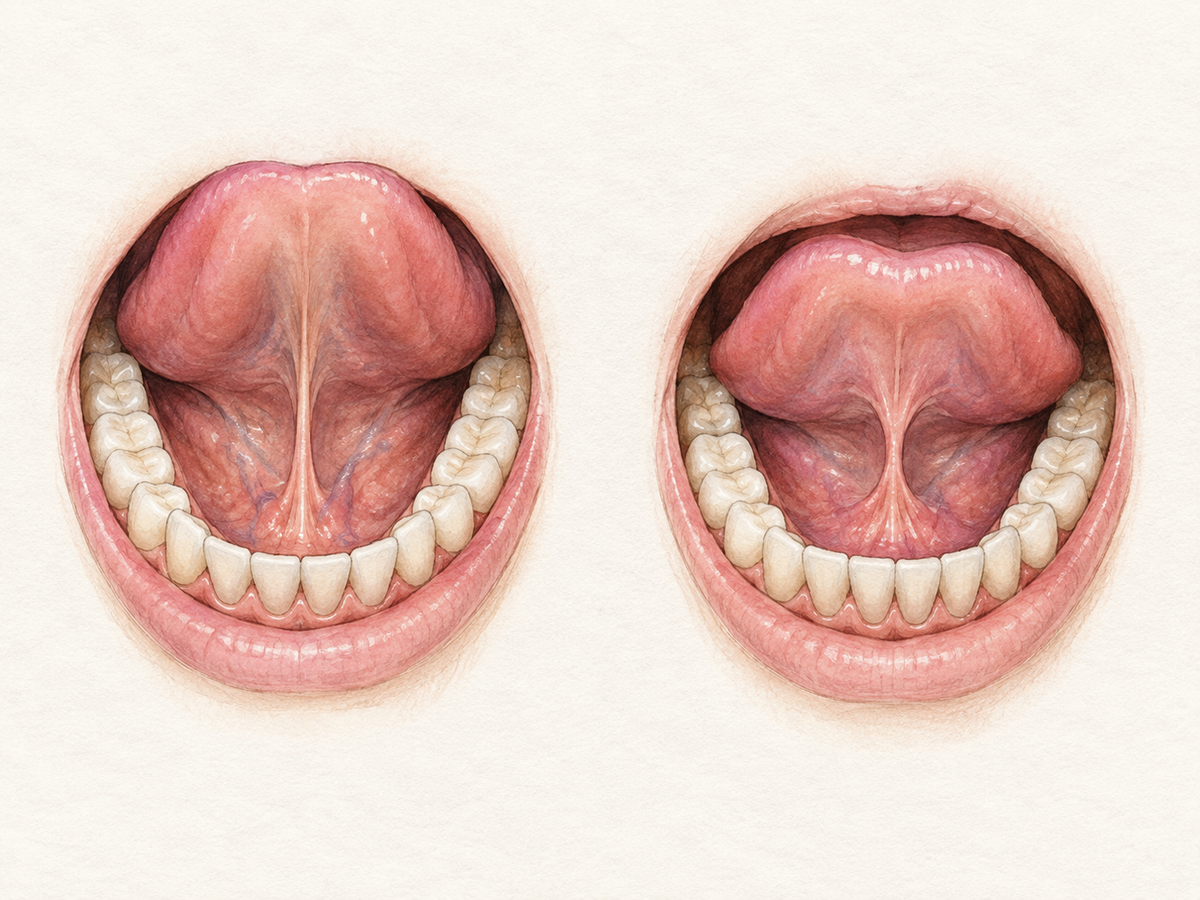
- The lingual frenum, under the tongue.
- The maxillary labial frenum, under the upper lip.
- The mandibular labial frenum, under the lower lip.
Most frenums never cause trouble. A short, thick, or tightly attached frenum may restrict movement, but that does not automatically mean it needs treatment. In fact, pediatric guidance notes that lip and cheek frena are normal oral structures and are not clearly related to breastfeeding mechanics (American Academy of Pediatrics clinical report).
Problems a Tight Frenum Can Cause
A tight lingual frenum is often called a tongue-tie. The medical term is ankyloglossia. It can limit how far the tongue can lift, extend, or move side to side.
Possible problems vary by age:
- Infants: Breastfeeding or latch pain, nipple soreness, clicking sounds, or poor milk transfer.
- Children: Trouble making certain speech sounds, or difficulty moving food around the mouth.
- Adults: Gum recession, a gap between the front teeth, limited tongue movement, or discomfort with a denture.
But there is an important caution: many infants with a tongue-tie feed well without any procedure. A diagnosis should be based on symptoms and a physical exam, not appearance alone. There is also no single accepted test for tongue-tie, and experts disagree on how to define it (American Academy of Pediatrics clinical report).
For adults, a upper lip frenum is often blamed for a gap between the front teeth, but the connection is not clear-cut. Many gaps close on their own as adult teeth come in, and frenectomy alone is usually not enough to close a gap (review on maxillary labial frenectomy).
Frenotomy vs. Frenectomy
The terms sound similar, but they describe different procedures.
| Procedure | What it is | Common use |
|---|---|---|
| Frenotomy | A simple clip or release of the tight band. | Often used for infants with a simple tongue-tie. |
| Frenectomy | A more complete removal or reshaping of the frenum. | More often used for older children and adults. |
A frenotomy may take only seconds to a few minutes in an infant. A frenectomy may take longer and may require stitches.
Providers sometimes use the terms interchangeably. If surgery is planned, ask exactly what will be done, what tool will be used, and whether stitches are expected.
Who Needs Treatment—and Who Doesn’t
Not every tight frenum needs surgery.
The evaluation should focus on function: how well the tongue or lip moves and whether that movement causes real difficulties. Depending on age and symptoms, the person may be assessed by:
- A dentist or oral surgeon.
- An ear, nose, and throat specialist.
- A lactation consultant for infant feeding concerns.
- A speech-language pathologist for speech or swallowing concerns.
Non-surgical options are often enough. These may include:
- Breastfeeding support or help with latch and positioning.
- Speech therapy.
- Orthodontic treatment for a gap.
- Denture adjustment.
- Simply watching and waiting.
There is also concern that tongue-tie has been overdiagnosed in recent years. Diagnosis and frenotomy rates have increased sharply, but the evidence for treatment is still mixed (American Academy of Pediatrics clinical report).
For infants, one review found that frenotomy may reduce nipple pain in the short term, but the effect on infant feeding is not consistent (Cochrane review). That is why a full feeding assessment should come first.
What Happens During the Procedure
Pain control depends on age.
- Infants often receive only a topical numbing gel or sugar solution for comfort.
- Older children and adults usually receive a local numbing injection.
The release may be done with surgical scissors, a scalpel, or a laser. Some studies suggest laser may cause less early pain and bleeding, but the evidence is limited and mixed (systematic review on laser frenectomy). No single tool has been proven best for everyone.
A simple infant frenotomy may take seconds to a few minutes. A frenectomy in an adult may take longer and may involve a few stitches. Most people can return to normal activities quickly, though the mouth may feel sore.
Recovery and Aftercare
Common healing signs include:
- Mild soreness or discomfort.
- Slight swelling.
- A white or yellow healing patch at the site.
- Minor bleeding for a short time.
These are usually normal. Aftercare may include gentle oral hygiene for adults and special feeding guidance for babies.
Stretching advice varies. Some providers recommend gentle tongue or lip stretches, while others say the evidence does not support routine post-procedure stretches. The American Academy of Pediatrics notes that post-operative stretching exercises are not evidence-based and are not recommended (clinical report). Still, follow your own provider’s instructions, because they know the exact procedure and your situation.
Call the clinician if you notice:
- Bleeding that does not stop with gentle pressure.
- Fever.
- Increasing pain or swelling.
- Signs of infection, such as pus or spreading redness.
Risks, Benefits, and Alternatives
The possible benefits of frenotomy or frenectomy include:
- Better infant latch and less nipple pain.
- Improved tongue or lip movement.
- Easier speech or eating for some people.
- Better denture fit or easier cleaning in select cases.
The possible risks include:
- Bleeding.
- Infection.
- Scarring or reattachment.
- Recurrence of the tightness.
- Rare damage to nearby structures, such as a salivary duct.
Serious complications appear uncommon, but they have been reported (FROSTTIE trial).
For non-urgent cases, a second opinion is reasonable. Ask:
- What exact procedure is planned?
- What problem is it expected to improve?
- What are the non-surgical options?
- What will it cost, and will insurance cover it?
- How much experience does the provider have with this procedure?
Bottom Line
A frenum is normal tissue. A tight one can limit tongue or lip movement and cause real problems, especially with infant feeding. Frenotomy or frenectomy can help selected people when symptoms justify it. But the evidence is mixed, and many people do fine without surgery. Talk with a qualified provider, consider non-surgical options first, and weigh the benefits, risks, and alternatives before deciding.
This article has been reviewed by an oral health professional for accuracy. It is intended to provide general educational information and should not be used as a substitute for personalized medical advice, diagnosis, or treatment. If you have questions or concerns about your oral health, please consult a dentist, physician, or other qualified healthcare provider.